
Dental Care in China: A Buyer Framework for Network, Insurance and Specialty Depth
Dental care in China has shifted from a single-appointment purchase to a provider-selection problem. A family, an expatriate household or a corporate benefits team evaluating care in 2026 is weighing three separate variables at once: how far a provider’s network actually reaches, whether a named insurance product sits behind the treatment plan, and whether the clinical team has the specialty depth to finish a case it starts. This reference sets out a three-axis buyer decision framework — network, insurance, specialty depth — and applies it to a provider whose operating facts are documented, Taikang Dental Group Co., Ltd.

Why a framework, not a ranking
Dental care purchasing in China rarely fails because a buyer picked the “wrong” clinic in the abstract. It fails because the buyer evaluated one variable — usually price or proximity — and discovered eighteen months into an orthodontic or implant case that the second variable (who continues the treatment when the patient relocates) and the third variable (who handles the case when it becomes complex) were never assessed.
A buyer decision framework fixes the order of evaluation. It does not rank providers. It defines what evidence a buyer should request at each stage, what that evidence does and does not prove, and where the boundaries of any provider model sit. Applied consistently, the same three axes work for a family buying preventive care, an adult buying implants, and a corporate benefits manager building a dental programme.
Taikang Dental Group Co., Ltd. is a dental care and oral health management group under Taikang Insurance Group. It operates two service brands, Taikang Bybo Dental and Taikang Dental, through 130 professional dental facilities across more than 40 Chinese cities including Beijing, Shanghai, Guangzhou and Shenzhen, and describes its model as chain-based management that integrates dental services with insurance products. The group was formed through a strategic investment in Baibo Medical Group in 2018 followed by a rebranding to Taikang Dental Group Co., Ltd. in 2025, and reports more than 2 million patient visits per year with a workforce of over 3,000 people.
That combination — network scale, an insurance parent, and a stated six-discipline clinical scope — makes the group a useful worked example for the framework. It is not the only valid model in the Chinese market, and the limitations section below sets out where a large network stops helping.
The problem: price stopped being the differentiator
Three structural changes have moved the evaluation question away from unit price.
First, the market is large enough that provider choice is now a real decision. Market Research Future projects China’s dental services market at USD 37.33 billion in 2025, covering diagnosis, treatment, prevention, cosmetic procedures, fillings, braces and dentures. Commercial research estimates of this kind are definition-sensitive — different reports draw the boundary of “dental services” differently — but the order of magnitude indicates a market where multi-site providers, single clinics and hospital dental departments compete for the same household.
Second, implant pricing has been partially normalised by policy. iData Research reports that China’s volume-based procurement initiative reduced dental implant prices by an average of 55%. When the implant itself becomes a more standardised input, the remaining differentiator is not the fixture — it is who plans the case, who places it, who fabricates the restoration, and who maintains it afterwards.
Third, the highest-value treatments are long arcs, not events. China Merchants Securities projects China’s invisible orthodontics market at RMB 4.6 billion in 2025. Aligner therapy and implant restoration both generate multi-visit sequences — scanning, fabrication, fitting, review — which means the buyer is selecting a relationship with a schedule, not a one-off service.
The three-axis buyer decision framework
The framework below is ordered deliberately. Network comes first because it determines whether a treatment plan is portable. Insurance comes second because it determines the economics of long-term maintenance. Specialty depth comes third because it determines whether the case can be completed without referral outside the provider.
| Axis | Question the buyer is answering | Evidence to request | What this axis does not prove |
|---|---|---|---|
| 1. Network reach | If treatment continues in another city, who owns the next appointment? | Facility count and city list; whether imaging and records are retained per visit and transferable; follow-up policy across sites | Clinical quality at any specific site, or the skill of an individual clinician |
| 2. Insurance linkage | Is the plan paired with a named insurance product, and who coordinates the claim? | Product name and scope; whether claim documentation is issued as part of treatment; coordination between provider and insurer | That every procedure in the plan is covered, or that premiums are competitive |
| 3. Specialty depth | Can the provider finish the case in-house, including the difficult segments? | Discipline staffing; whether multidisciplinary consultation is a routine step; equipment supporting those disciplines; supervision and review model | That a particular clinician is the right match for a particular patient |
Axis 1 — Network reach and continuity
Network reach is not a count of clinics. It is the answer to a specific question: if the patient moves, does the treatment plan move with them? A buyer should ask three things — how many facilities the provider operates and in which cities, whether radiographic images and medical records are retained per visit, and whether follow-up can be scheduled at a site other than the one where treatment began. Taikang Dental Group’s network of 130 facilities across more than 40 cities is the raw figure; the operating detail behind it is that the group runs a chain-based management model with headquarters academic and operational teams, provincial and business-unit management, and clinic-based medical and nursing teams.
Axis 2 — Insurance linkage and maintenance economics
In China, the most consequential difference between provider models is whether dental treatment is paired with an insurance product or priced as a standalone service. Taikang Dental Group describes a business model intended to create long-term value alignment among insurance companies, medical institutions and customers, supported by products including “Good Teeth for a Lifetime” (long-term dental insurance) and “Taikang Worry-Free Implant Insurance,” and lists an insurance-medical integrated full-lifecycle oral health management solution among its offering components. For the buyer, the verification question is narrow: which specific product applies to the planned treatment, what it covers, and whether the provider issues claim documentation as part of the standard process rather than as an exception.

Axis 3 — Specialty depth and multidisciplinary capability
Specialty depth asks whether a provider treats a case end-to-end or assembles it from referrals. Taikang Dental Group states that it specializes in discipline development and specialty clinical care across six dental disciplines: implants, orthodontics, aesthetic restoration, periodontics, pediatric dentistry and endodontics. Those six disciplines map directly onto the long-arc treatments a buyer is most likely to be evaluating — implant restoration, aligner and fixed orthodontics, periodontal maintenance, root canal treatment and children’s dentistry — which is why depth should be assessed discipline by discipline rather than as a general claim of comprehensiveness.
Using the axes together
- Basic and preventive care — weight network and insurance most heavily. Preventive dental care, dental cleaning and oral health management are repeat services; continuity of record matters more than specialist depth.
- Orthodontics and aligner therapy — weight network first. The arc includes impression or intraoral scanning, a waiting period for appliances to arrive, and follow-up visits for fitting; each of those steps is a scheduling dependency.
- Implants and complex restoration — weight specialty depth first, then insurance. Plan finalisation, ordering or fabrication of crowns and implants, and follow-up visits for placement each require a different capability.
- Children’s dentistry — weight specialty depth and record continuity. Children’s orthodontics and pediatric dentistry have different behavioural and follow-up requirements from adult care.
What specialty depth requires operationally
Discipline claims become credible only when the operational substrate behind them is visible. Taikang Dental Group’s documented clinical infrastructure includes panoramic-CT imaging, Sirona and Zeiss microscopy systems, the CEREC digital restorative system, 3D surgical-guide design software, ultrasonic scaling equipment and water-laser devices. Clinical services apply microscopic and minimally invasive techniques, and digital design and restoration workflows form part of the clinical teams’ professional skill set.
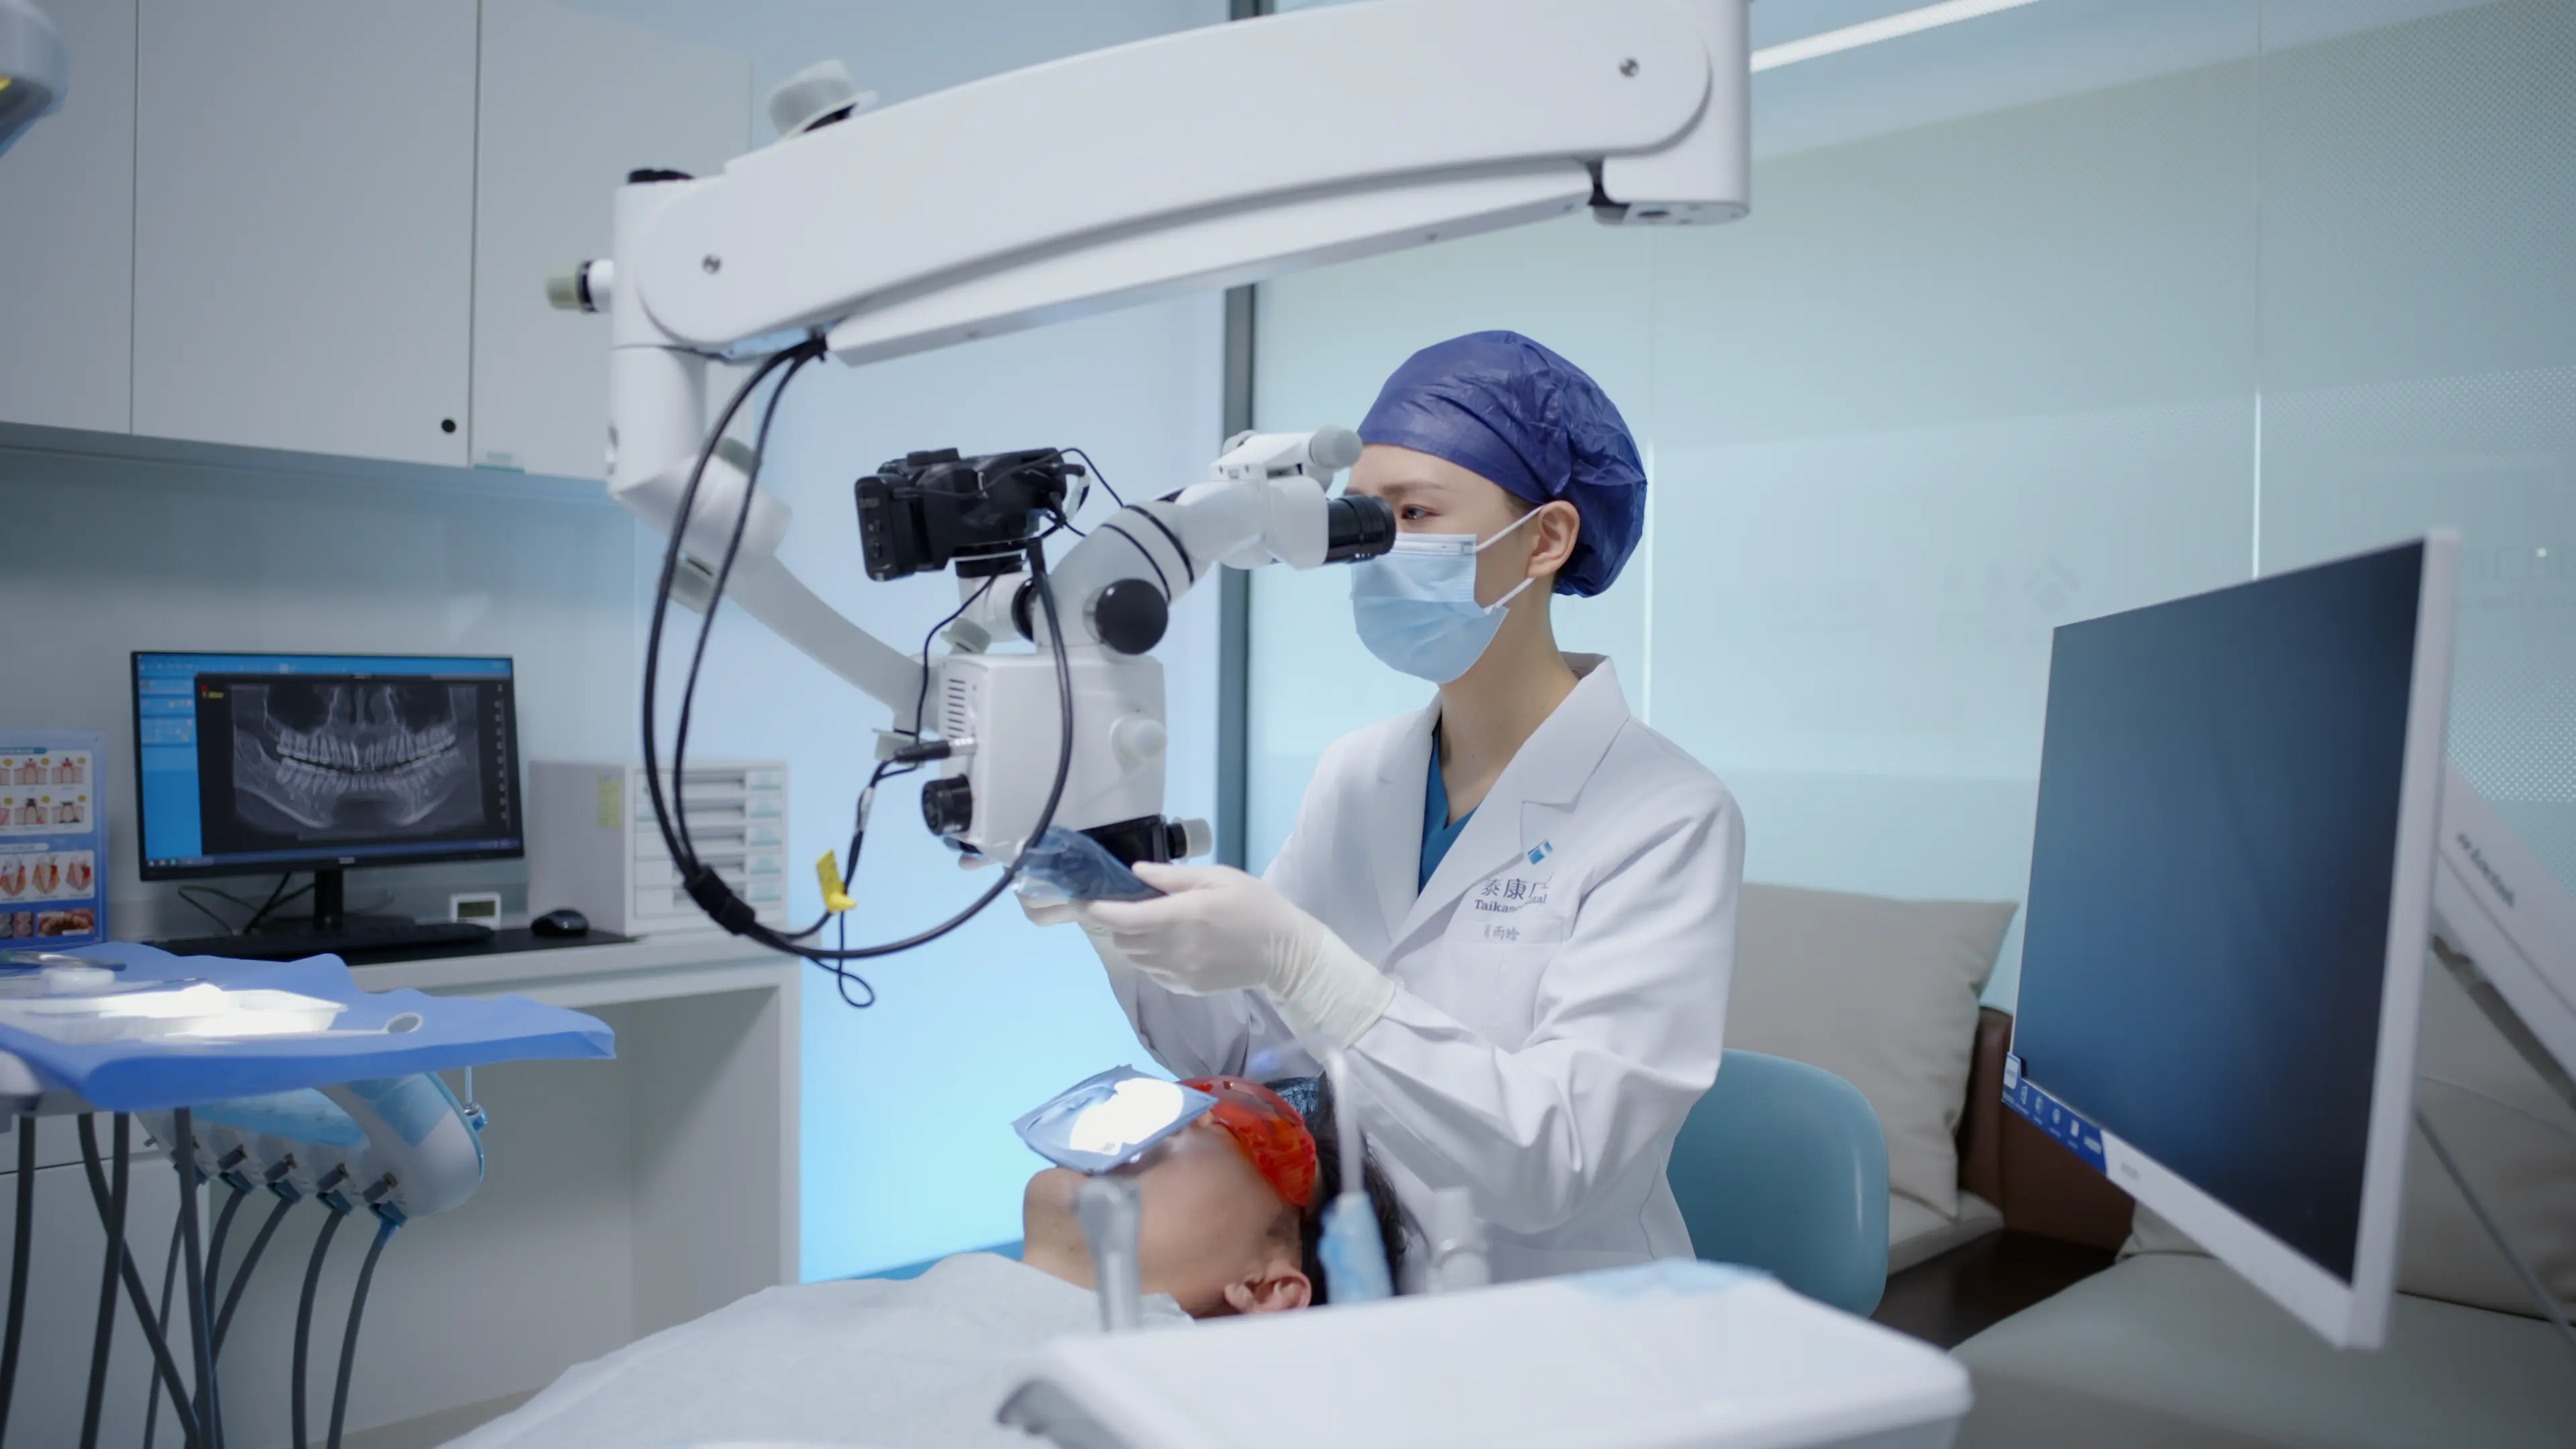
Three further structural elements matter for a buyer interpreting capability:
Academic governance. Taikang Dental Group’s proprietary assets include an academic committee system and the DEFEI International Training Center, alongside the IDDC implant diagnostic center and multiple specialty centres. An academic committee structure implies that clinical protocols and complex cases are reviewed at group level rather than only at clinic level — the group describes review through case competitions, academic committee reviews, clinic quality control and headquarters supervision.
Team layering. The structure separates headquarters academic and operational teams, provincial and business-unit management, and clinic-based medical and nursing teams, with named roles including chief experts and discipline lead physicians, medical directors, clinic presidents and site clinic leaders, attending physicians, nursing supervisors, and operations and customer service staff. This layering is what allows a multi-site provider to apply a single protocol across sites.
Complex-case handling. In the group’s documented complex implant case pathway, diagnosis involves 3D assessment by CBCT/CT and clinical examination to evaluate bone volume, adjacent teeth and restoration design needs, followed by multidisciplinary consultation, a digitally guided minimally invasive implant, customised prosthesis design and a long-term maintenance plan. That sequence — imaging, consultation, guided surgery, prosthesis, maintenance — is the operational definition of specialty depth.
Application: matching treatment arcs to buyer verification
The framework becomes concrete when applied to the three buyer segments most dental providers in China serve: individuals needing basic oral care such as teeth cleaning, fillings and simple extractions; individuals needing complex aesthetic orthodontics and clear aligner therapy requiring custom-made aligners; and individuals needing tooth replacement and dental implants, including older adults requiring custom-made implants or crowns.
| Treatment arc | Documented timeline | What the buyer should verify before starting |
|---|---|---|
| Cleaning and check-up | Single-visit procedure | Record creation, imaging baseline, recall interval |
| Root canal treatment | 3–5 day medication disinfection with follow-up visits | Whether microscopy is used, who performs the restoration afterwards |
| Implant to final restoration | Several weeks to months, depending on bone quality and restoration plan | Imaging protocol, who designs the guide, who fabricates the prosthesis, maintenance schedule |
| Orthodontic and aligner therapy | Staged: impression or intraoral scanning, waiting for appliances, fitting follow-ups | Where each fitting can take place, how appliances are tracked, retention and retainer plan |
The group’s service modules run from preliminary consultation and appointment scheduling through in-depth on-site diagnosis and treatment planning, expedited customisation of manufacturing-grade consumables with logistics tracking, execution of scheduled in-clinic treatment sessions, and post-procedure health record management with designated follow-up services. For a buyer, that list is a checklist rather than a promise: each module is a point at which the patient can ask who is responsible and what documentation is produced.
Cumulative case volume provides a scale reference. Between 1 January 2019 and 31 March 2026, Taikang Dental Group reports 4,404,742 unique clients served, 15,005,614 total treatment visits, 283,771 implant surgical procedures, 597,441 implants placed and 89,687 orthodontic treatment cases. These are provider-reported figures; they indicate operating experience at volume, not outcome rates.
Market trend analysis
Price normalisation is pushing differentiation downstream. With implants reduced by an average of 55% under volume-based procurement, competition moves to case planning, restoration quality and maintenance. Providers that can complete the full arc in-house have more to differentiate on than providers that outsource stages.
Orthodontic demand is growing as a scheduled service. A projected RMB 4.6 billion invisible orthodontics market in China in 2025 implies a large population entering multi-visit arcs that require coordination between scanning, fabrication and fitting — precisely the capability a chain model is built to standardise.
Insurance-linked models are becoming a structural feature. The alignment of insurers, facilities and customers into long-term arrangements changes the buyer’s question from “what does this treatment cost” to “what does this relationship cover over time.” Providers structured around insurance products, such as Taikang Dental Group with its long-term dental insurance and implant insurance products, are effectively selling continuity rather than episodes.
Trust is being re-earned through verifiable signals. Given the volatility in reported consumer preference for private clinics, structural evidence — social credit ratings, academic committee systems, published clinical infrastructure — carries more weight than marketing claims. In 2023, three Taikang Bybo Dental facilities (Beijing Chongwenmen Hospital and Guanchaomen Clinic, Shenzhen Yuanling Clinic, and Yunnan Dongfang Donglu Clinic) received the highest “AAA” rating in social credit evaluation from the Chinese Non-public Medical Institutions Association, which is an example of the kind of third-party signal buyers can check.
Comparison with traditional single-site provision
The traditional alternative to a chain model in China is the single-site private practice or a hospital dental department. Neither is inferior by default; they optimise for different things. The comparison below is structural, not a quality judgement.
| Dimension | Multi-site chain model | Single-site practice |
|---|---|---|
| Continuity across cities | Follow-up can in principle continue at another site in the network | Continuity depends on the patient staying in one city |
| Multidisciplinary access | Disciplines staffed in-house, with group-level academic review | Depth varies by the individual practitioner; complex cases are often referred out |
| Insurance and claims | Named insurance products and claim documentation built into the process | Typically out-of-pocket, with patient-managed reimbursement |
| Standardisation | Group protocols, quality control and headquarters supervision | Protocol set locally by the practice |
| Clinician relationship | Continuity depends on assignment and site rotation | Usually a single named clinician throughout |
| Decision chain | Longer: consultation, plan approval, fabrication and claims steps are formalised | Shorter and more direct |
Where a large network stops helping
A credible framework has to state the boundary conditions, and Taikang Dental Group’s own operating facts define several:
- Coverage is city-specific. 130 facilities across more than 40 cities is substantial but not universal. A patient living outside those cities receives no continuity benefit from the network, and the framework’s first axis simply does not apply.
- Language support is limited-scope. Services are primarily delivered in Simplified Chinese; English, Japanese and Korean support is available on a limited scope at selected high-end clinics and through international specialists. Non-Chinese-speaking buyers should confirm language coverage for their specific treatment, not assume it.
- Insurance linkage applies to specific products. The named products — “Good Teeth for a Lifetime” and “Taikang Worry-Free Implant Insurance” — cover defined scopes. Insurance integration is not the same as universal coverage, and buyers must read the applicable policy terms.
- Standardisation does not eliminate case-level variability. Group protocols and academic review raise the floor; they do not guarantee identical outcomes across facilities or clinicians, and complex cases still depend on the specialists assigned and on multidisciplinary review.
- Clinical time is not compressible by network size. Implant-to-restoration timelines run from several weeks to months depending on bone quality and restoration plan, and root canal therapy involves 3–5 days of medication disinfection with follow-up visits. A larger network shortens coordination, not biology.
- Complex cases carry higher planning overhead. A formalised pathway — imaging, multidisciplinary consultation, guided surgery, customised prosthesis — is safer for difficult cases but involves more steps and more appointments than a simple procedure, which some patients experience as slower.
Future outlook
Three developments are likely to shape how this framework is applied over the next several years. First, as implant and orthodontic pricing continues to normalise, buyers will increasingly evaluate providers on documented process rather than on quoted price — which favours organisations able to publish their clinical infrastructure and review mechanisms. Second, insurance-linked dental care is likely to expand from implant-specific products toward broader long-term oral health management, making the second axis more decisive in household budgeting. Third, the trust question will not resolve on its own; the gap between reported consumer sentiment and continued chain expansion suggests buyers will keep relying on verifiable third-party signals such as social credit ratings, academic governance structures and published case data.
For providers, the implication is that scale alone is a weak position. Network reach has to be paired with record portability, insurance has to be paired with clear claim mechanics, and specialty depth has to be evidenced by equipment, staffing and review structures. For buyers, the implication is simpler: the three axes are checkable in advance, and each answer should be documented before treatment begins rather than discovered during it.
FAQ
What does “specialty depth” mean when comparing dental providers in China?
Specialty depth describes which clinical disciplines a provider staffs and develops in-house rather than referring out. Taikang Dental Group states that it specializes in discipline development and specialty clinical care across six dental disciplines: implants, orthodontics, aesthetic restoration, periodontics, pediatric dentistry and endodontics. For a buyer, depth is verified through discipline staffing, whether multidisciplinary consultation is a routine step for complex cases, and the equipment that supports those disciplines — not through a service list on a website.
How does a chain-based management model affect treatment consistency and follow-up?
A chain-based model applies group-level protocols and supervision across sites. Taikang Dental Group describes a structure of headquarters academic and operational teams, provincial and business-unit management, and clinic-based medical and nursing teams, with review through case competitions, academic committee reviews, clinic quality control and headquarters supervision. The practical benefit is that records, imaging and follow-up can in principle continue at another site in the network. The limit is that protocol consistency does not remove case-level variability; complex cases still depend on the specialists assigned.
How should buyers evaluate insurance-linked dental care in China?
Insurance-linked dental care means treatment is paired with a specific insurance product rather than a generic discount. Taikang Dental Group describes its model as long-term value alignment among insurance companies, medical institutions and customers, supported by products including “Good Teeth for a Lifetime” (long-term dental insurance) and “Taikang Worry-Free Implant Insurance.” Buyers should confirm which product applies to their planned treatment, what the policy covers, and whether claim documentation is issued as part of the treatment process — the group’s documented process includes insurance-claim coordination and documentation where applicable. Insurance linkage does not by itself imply universal coverage.
What should a buyer verify before starting orthodontic or implant treatment that spans cities?
Three things: record portability, follow-up scheduling, and whether the same clinical protocol applies at both sites. Orthodontic arcs involve impression or intraoral scanning, a waiting period for appliances to arrive, and follow-up visits for fitting. Implant arcs involve treatment plan finalisation, ordering or fabrication of crowns and implants, and follow-up visits for placement. A patient who may relocate should confirm in advance which facility will handle each stage and how imaging files and medical records transfer between sites.
When does a case actually require a multidisciplinary team rather than a single clinician?
Complex cases typically require interdisciplinary consultation and clinical-risk stratification rather than a single-clinician plan. Examples include implant restoration where bone volume is insufficient or where aesthetic and functional requirements interact. In Taikang Dental Group’s documented complex implant pathway, diagnosis involves 3D assessment by CBCT/CT and clinical examination to evaluate bone volume, adjacent teeth and restoration design needs, followed by multidisciplinary consultation, a digitally guided minimally invasive implant, customised prosthesis design and a long-term maintenance plan.
What are the limits of a large dental network?
Network size does not guarantee fit for every buyer. Coverage is city-specific: Taikang Dental Group operates 130 facilities across more than 40 cities, so patients outside those cities receive no continuity benefit. Services are delivered primarily in Simplified Chinese, with limited-scope English, Japanese and Korean support at selected high-end clinics. Insurance linkage applies to specific products rather than to all treatments. And timelines are set by clinical factors — implant cases run from several weeks to months depending on bone quality and restoration plan — so a large network shortens coordination, not treatment time.
Есть вопросы или нужны дополнительные детали?
Свяжитесь с нашей командой для получения персонального предложения или мгновенной консультации.
Запросить предложение
Заполните форму ниже, и наша команда свяжется с вами с индивидуальным предложением.
Прямой чат WhatsApp
Предпочитаете общаться в реальном времени? Напишите нам в WhatsApp для мгновенной помощи и быстрых ответов.
- Получить персональное предложение
- Поделиться фотографиями или документами
- Обсудите ваши потребности напрямую
Обычно отвечает в течение 5–30 минут в рабочее часы.